
Mechanism of Action Series : This series of articles in clinical endocrinology is designed for endocrinology fellows interested in gaining a better understanding of endocrine pathophysiology. These carefully selected concise articles are part of our “Understanding endocrine pathophysiology series”
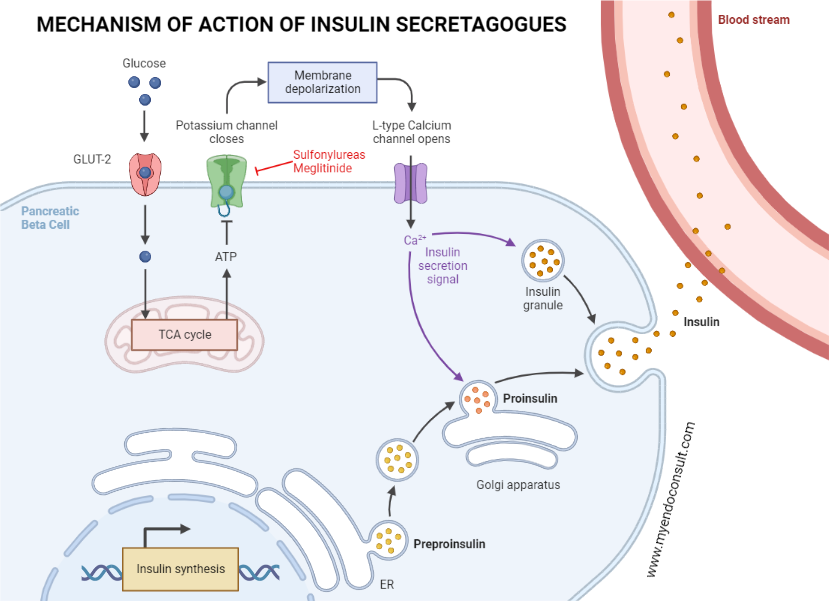
Why this series in endocrine pathophysiology?
- We have sought to present endocrine pathophysiology in a manner that emphasizes more practical concepts compared to traditional textbooks on the topic. This text facilitates an integrated approach to learning endocrine pathophysiology through an appreciation of the mechanism of action of medical therapies. Relevant endocrine physiology is presented before a detailed description of the mechanism of action of selected medical interventions. Several illustrations and well-annotated line diagrams are used to enhance an efficient review of basic and advanced endocrine pathophysiology concepts. Also, clinical pharmacology pearls (side effects and therapeutic monitoring guidelines) are emphasized where applicable.
- Clinical practice guidelines change over time as our knowledge of disease states evolves. Endocrinology is a complex subdiscipline of internal medicine characterized by a rapid turnover of knowledge. As a result, we have avoided emphasizing guideline-defined treatment protocols in favor of the pathophysiologic basis of endocrine therapies. This series of articles is by no means exhaustive concerning endocrine pathophysiology. We, however, hope that a discussion of various endocrine therapies will facilitate a better appreciation of complex concepts in endocrine physiology in a more clinically relevant manner.
- Also, endocrinology fellows and practising physicians should be familiar with landmark clinical trials in the field. We have made a concerted effort to highlight practice-changing clinical trials where relevant. We hope this will enrich the training of not only endocrinology fellows but also internal medicine residents, medical students, and other allied health professionals such as pharmacists, nurse practitioners, and physician assistants.
- We welcome feedback from our web audience regarding the limitations of this series and look forward to incorporating valuable suggestions in future editions. The MyEndoConsult team went through painstaking efforts to create this series of articles and welcome suggestions for improving it.
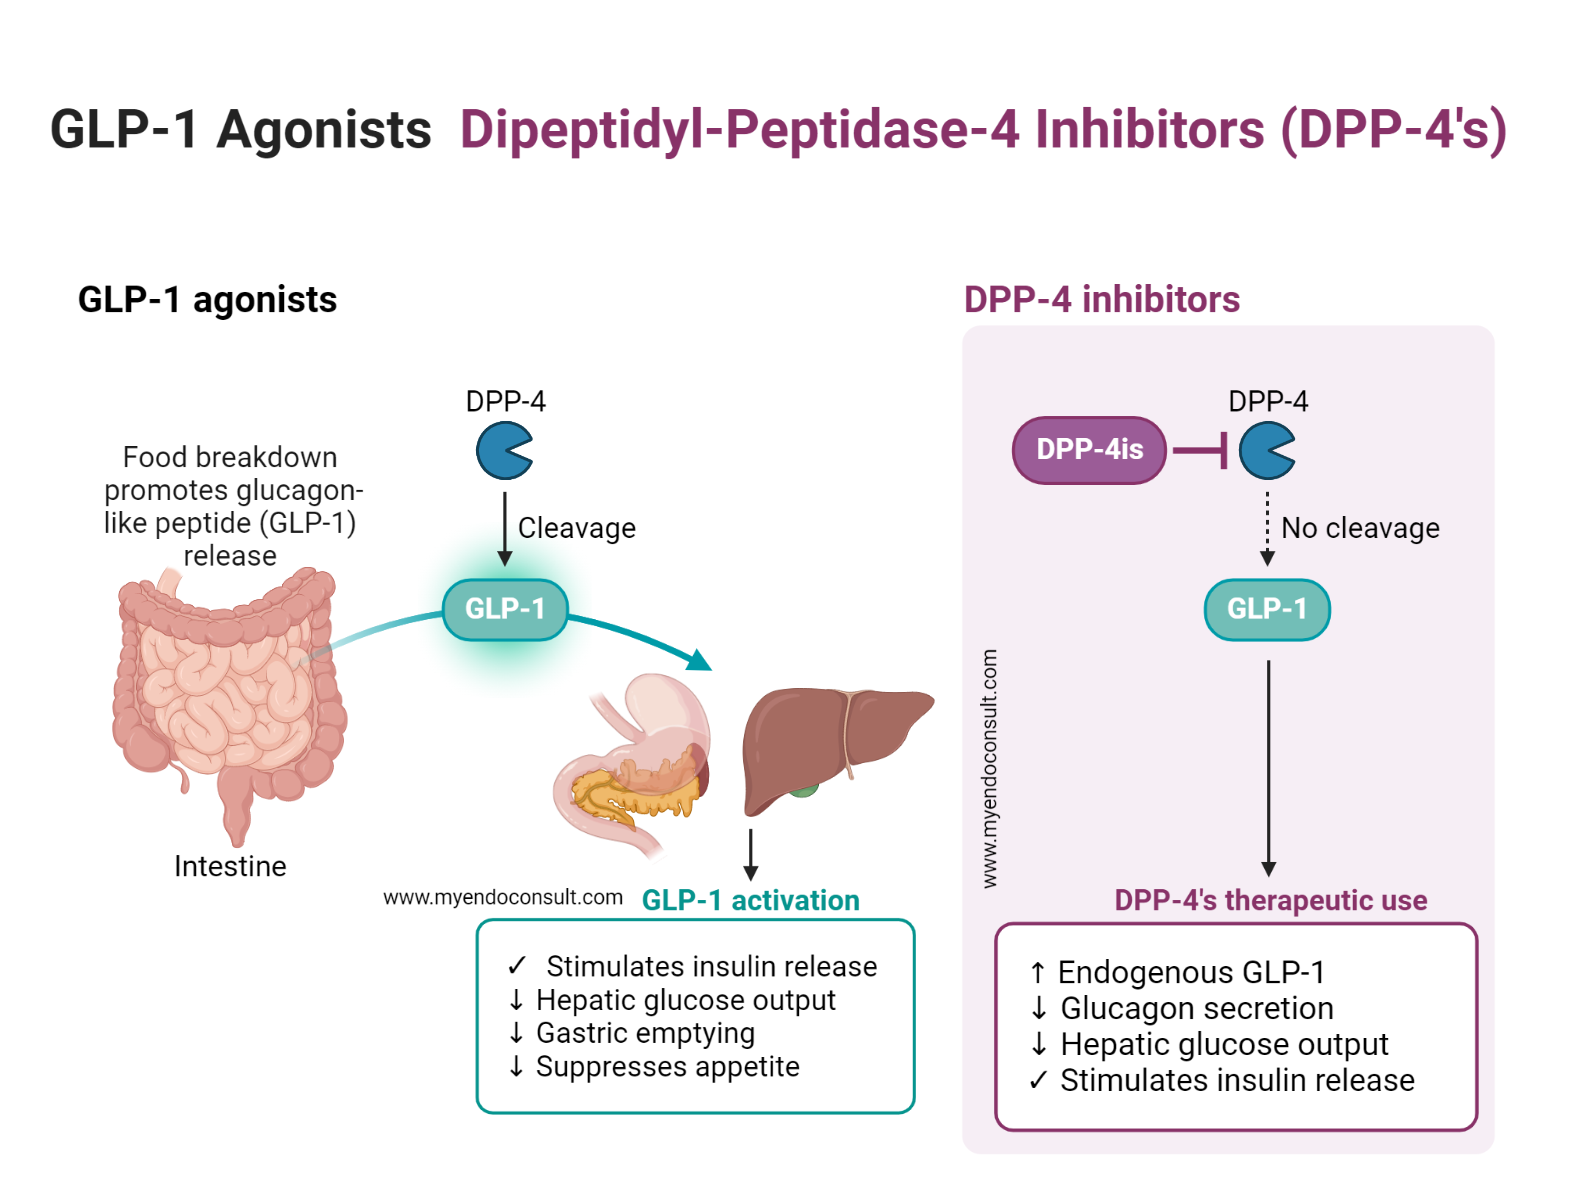
Insert Featured Content List
Repaglinide Mechanism of Action
Metformin Mechanism of Action
Mechanism of action of inclisiran (leqvio)
Mechanism of Action of Insulin
Ezetimibe Mechanism of Action
Cinacalcet Mechanism of Action
Page [tcb_pagination_current_page] of [tcb_pagination_total_pages]